








Thirty years ago, a small startup team of scientists in Boston published findings that began with the venom of a Gila monster and ended in a weight-loss revolution.
The breakthrough discovery — glucagon-like peptide compounds (GLP-1s) showed promise as a treatment for diabetes and obesity — was largely ignored. Pfizer pulled the researchers’ funding and sold off the license. Discovery doesn’t guarantee medical progress — or market success.
Not until 2021 did Novo Nordisk introduce Wegovy, touching off a GLP-1 boom. According to Gallup, 11 percent of US adults now report taking a GLP-1 medication for weight loss: a quadrupling over the past two years.
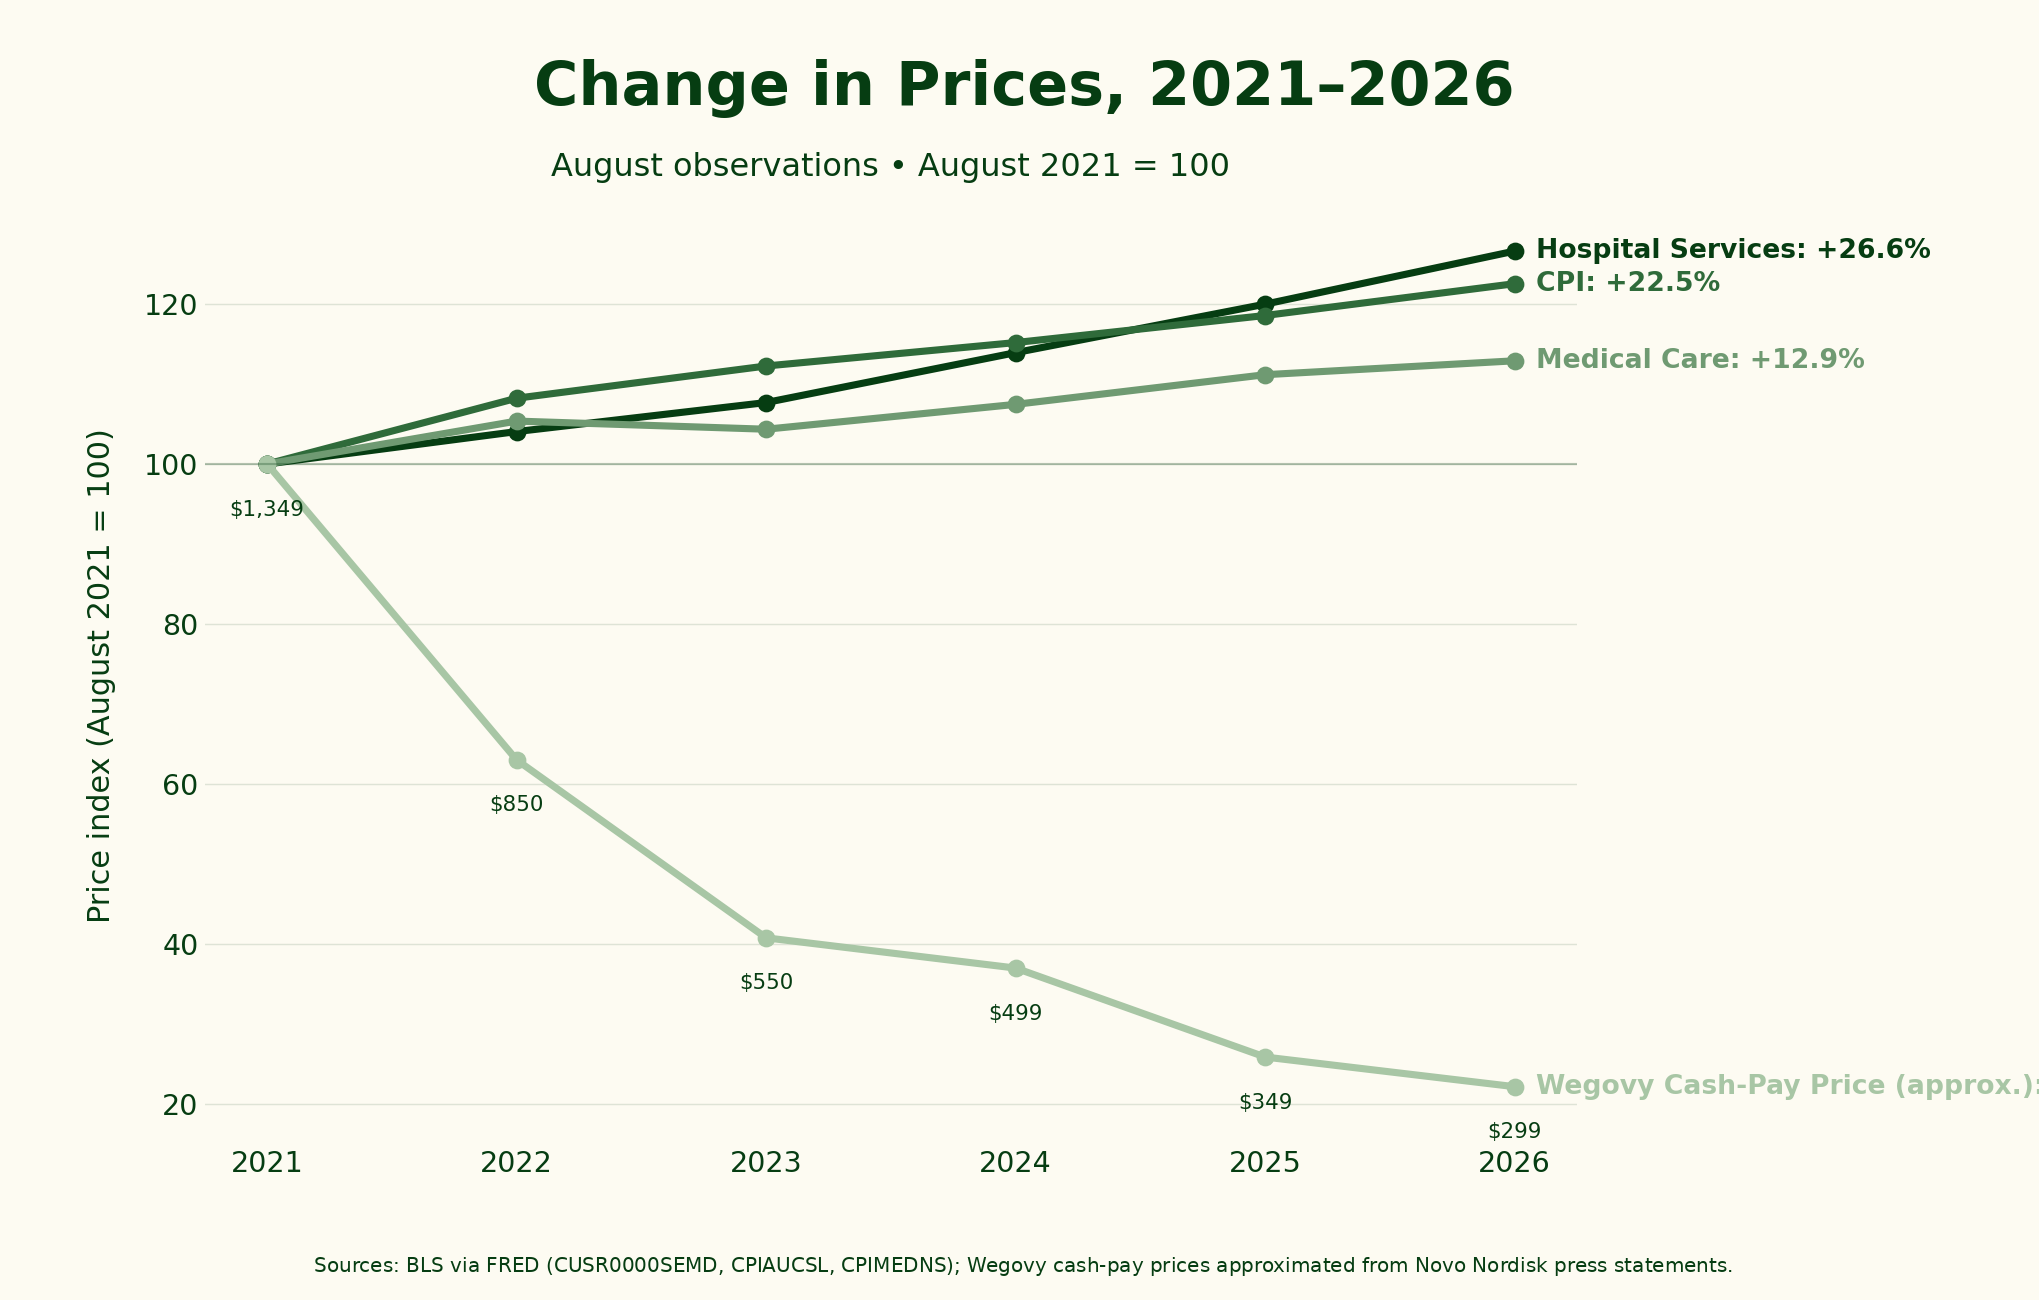
John Puri at National Review credits capitalism and innovation for transforming this scientific breakthrough into greater abundance. Coverage by insurers remains limited — and cash prices have fallen around 75 percent since 2021.
When Wegovy’s one-of-a-kind treatment debuted in 2021, a month’s supply cost $1,349. At the time, blue-collar employees were earning an average of $26.12 an hour, putting the time-price at 51.65 hours per month, or more than six days’ wages.
Employer insurance plans balked, and the government’s health programs were barred from covering weight-loss drugs unless there was a specified medical complication. More than half of American adults (137 million) meet the medical criteria to benefit from the FDA’s approved uses of GLP-1s: the cost of covering them all is enormous.
Even with mostly cash payers, demand outstripped supply, putting Wegovy on the FDA’s drug-shortage list. With that designation came a legal path for pharmacies to compound the product themselves, and offer lower-priced alternatives through telehealth and cash-pay programs.
Two years later, a second major company gained FDA approval for an injectable drug for chronic weight management. Eli Lilly’s Zepbound is pharmacologically different, but its effects are similar and it competes for the same patients and insurer budgets. The list price undercut Wegovy, at $1,060.
Here’s where things really get interesting.
Competition for Cash Patients Crashes Prices
Eli Lilly knew few of the potential beneficiaries of its medication would qualify for the medication through their insurers. So it offered a special $550 cash price for patients whose insurance didn’t cover GLP-1s. In 2024, it launched LillyDirect: a direct-to-consumer, cash-pay distribution for its competing product. Direct-to-consumer cash-pay pathways allowed patients to bypass asking “which drug does my insurance cover?” and forced manufacturers to compete in a more retail-like environment.
And compete they did. Novo Nordisk introduced its own cash-pay option for Wegovy — NovoCare. Its lowest dose was priced at $499/month. In April 2025, with the FDA’s shortage resolved and still facing innumerable gray-market and privately compounded copies of semaglutide, Wegovy’s price was reduced again, to make the authentic brand more price-competitive for patients, who Novo knew could easily switch. Standard self-pay injectable Wegovy dropped to $349/month, with a $199/month introductory offer.
In response, Eli Lilly cut Zepbound’s cash pricing, offering the typical maintenance dose for $299 by December 2025. Prescribers and patients became more comfortable switching between major branded therapies that filled essentially the same medical need. That increased the price pressure on drugmakers who were accustomed to negotiating with insurer formularies and formal rebate systems.
Almost immediately after Zepbound’s price reduction, the FDA approved an oral formulation of Wegovy. Clinical trials show the once-a-day pill is almost as effective as the injectable, and the pill form expands the available market to include patients unwilling to self-inject GLP-1s.
Today, the oral maintenance dose of brand-name Wegovy costs $299 a month for self-paying patients. Self-pay pricing for injectable Wegovy settled at $349. Fifty percent of sales of both Wegovy and Zepbound are direct exchanges with cash-paying patients.
Our “average” blue-collar worker from 2021 is now earning $32.53/hour. The time price of his monthly weight-loss treatment has fallen by 75 to 80 percent.
Over the same period, according to BLS reports, hospital services have risen 26.6 percent, and medical care prices, 12.9 percent. Overall consumer inflation (CPI) has increased 22.5 percent.
The official monthly list price for Wegovy remains $1,349 per month in 2026, unchanged from its launch baseline.
So Does Wegovy Cost $1,349 or $299?
That vast discrepancy between “official” pricing for pharmacies and commercial insurers and the cash-pay price tells us an interesting story about how competition lowers price — and what gets in the way.
Traditional health insurers have been hesitant to cover these expensive drugs for “cosmetic” weight loss, even as evidence of their effectiveness mounts. Fewer than one in five employers with 200 or more workers cover GLP-1s for obesity, citing long-term use and high costs. As the drugs’ popularity has exploded, the number of companies that are willing or can afford to cover them is likely to decline. Federal law prohibits Medicare Part D from paying for weight-loss prescriptions in the absence of a comorbidity like diabetes, and just one percent of individual Marketplace plans include access to GLP-1s.
With insurers and bureaucrats out of the way, GLP-1 makers are pricing directly for their end customers. That’s unusual for medical care, where insurers and government pay the bill and patients are insulated from the actual costs.
Economists call this the third-party payer problem. When end users of medical care are paying with someone else’s money, they have little incentive to shop around. Doctors and drugmakers who can only access patients in need if their treatments are “covered” end up viewing the bureaucrats as their customers.
Milton Friedman explained that under this “bureaucratization of medical care” the “caregiver has become, in effect, an employee of the insurance company or, in the case of Medicare and Medicaid, of the government.” What’s best for the patient becomes secondary, and “is often in direct conflict with the interest of the caregiver’s ultimate employer,” the insurer.
Falling GLP-1 prices offer a glimpse of what’s possible when third-party payers get out of the way. Competition gives consumers more choices. Competing brands have to adjust prices because they aren’t selling to insurers or the government, but to the end-user, spending her own money.
How “Free” Coverage Costs You More
Just because competition is bringing prices down doesn’t mean government will stay out of the market. Thirteen states now cover GLP-1s through their Medicaid programs, with the federal taxpayers ultimately matching the tab.
Medicare has gone further. In July 2026, CMS launched the Medicare GLP-1 Bridge to give eligible Part D beneficiaries access to Wegovy and a few competing GLP-1 drugs. CMS itself says the program sits outside ordinary Part D. Patients pay a $50 monthly copay, but participating manufacturers promised to provide the program drugs at a net price of $245 per monthly supply.
CMS has negotiated a small discount (CMS’s $245 net price is lower than the $299 retail cash price), but most of the cost has not disappeared; it has been shifted away from the person choosing the drug. The subsidy-and-copay model weakens the direct pricing mechanism that helped reduce cash prices in the first place. The user no longer confronts actual prices; taxpayers absorb much of the difference.
Breaking the direct-pricing function for temporary savings demonstrates what John Puri called the government’s “appetite for providing short-term relief at long-term expense.”
Unhappy Losers
Not everyone is celebrating our shrinking appetites. Creating new value in markets is often accompanied by destroying or displacing existing value. When consumer behavior changes as drastically as it has since the debut of GLP-1s, other industries will be forced to adapt. Welcome to the world of tradeoffs.
Food Dive reports that the increased adoption of GLP-1 drugs could “put $73 billion in brand value at risk.” If sales of appetite-suppressing medications soar, demand for calorie-dense snacks will drop. A Cornell study found one household member taking GLP-1s reduced family grocery spending 6 percent. Food giants like Doritos, Hershey’s, Cheetos, Kellogg’s and Reese’s are particularly vulnerable. By one analysis, an estimated 45 percent of Frito-Lay’s brand value is “at structural risk to the medications.”
It’s not just the snack aisle that’s feeling the pressure. GLP-1 drugs are also changing America’s drinking habits.
Ernst & Young reports that 44 percent of GLP-1 users cut back on beer, wine, and liquor after beginning treatment. Even after stopping treatment, 82 percent maintained their healthier (and less-spendy) habits.
Another big loser? Weight Watchers. The purveyors of traditional points-based dieting saw a cratering of demand after injectable GLP-1s became widely available. The company accumulated $1.1 billion in debt, lost a million members and 40 percent of its stock value, and filed for Chapter 11 bankruptcy.
That’s classic creative destruction. The same innovation that makes weight loss more affordable could make life considerably more difficult for companies selling potato chips, chocolate, and wine, as well as other families of weight-loss treatment. We’re still learning what GLP-1s can do: they soon could be disrupting businesses built on nicotine, gambling, drug and alcohol rehab, bariatric surgeries, and even Alzheimer’s care.
But prosperity is not measured by how much consumers must spend to get what they want. Innovation makes us all richer when it lets us accomplish more with fewer resources — even when doing so destroys the value of yesterday’s products and business models. And GLP-1s are making successful weight loss far more abundant, at ever-lower cost.


